
Crime prevention, public health surveillance, and disaster preparedness programs across the country are getting hit by federal funding instability and the end of COVID-era grants.
by Kim Bellware

The federal funding fallout is showing up in programs meant to keep communities safe. (David Alvarado/City Bureau)
“Perfect Storm” is a series focused on how federal funding instability is affecting local communities, produced by City Bureau in partnership with local organizations in the Documenters Network. It looks at how communities across the United States — big and small, rural and urban — are reckoning with slashes to federal budgets, the sunsetting of COVID-era grants, and turbulent legal challenges leaving funding in limbo. Find the full series here.
Documenters assignments from Karmeisha Boyd, Nikebia Brown-Joseph, Ava Grubb, Holland Harmon and Ruth Johnson, Katrina Herring, Zara Norman, Tema Zeldes-Roth (Chicago); Mikayla Coleman (Cleveland); Amy Spring (Columbia Gorge); Larae Baker and Asjah G. Banks, Sarah Galt, Sydnie Kelly, Ebony Williams, (Detroit); Tiffany Baron, Anna Hitz-Bradley (Indianapolis); Matthew Miuccio (San Diego); and Glen Johnson (Twin Cities) were used to help this reporting. Find more meeting coverage at Documenters.org.
When major events unfold in the Twin Cities, a parallel version often plays out at the Hennepin County Medical Center.
The sprawling facility in downtown Minneapolis spanning six city blocks is the area’s largest safety-net hospital and busiest provider of critical trauma care. HCMC is where measles outbreaks, COVID-19 surges, low-income patients and mass casualty events like last year’s Annunciation school shooting converge, said Jeremy Olson-Ehlert, a 13-year veteran nurse and member of the nurse’s union.
The hospital is so busy on some days, nurses have to shuffle patients in what he described as a “musical beds” arrangement.
“A lot of the issues stem from: People can’t afford healthcare. So where do they go? They go to us,” Olson-Ehlert said.
But despite the demand for services, HCMC has been gripped by fears of aggressive downsizing, or even outright closure. The hospital’s costs for providing care to low-income patients are soaring — and increasingly going uncompensated by the federal government.
When changes to Medicaid eligibility under H.R. 1, known as the “One Big Beautiful Bill Act,” take effect Jan. 1, as many as 140,000 low-income Minnesotans could lose healthcare coverage and send safety-net hospitals like HCMC over the brink. Already, financial pressures have pushed HCMC to implement a cap on patients, reducing patient beds by 20%, down to 390.

Women embrace at the memorial outside the Annunciation Catholic Church following a shooting at the school, Aug. 31, 2025, in Minneapolis. (AP Photo/Ellen Schmidt, File)
Minneapolis is among the tens of thousands of cities, counties and towns across the country being squeezed as three financial forces converge: The scheduled end of American Rescue Plan Act (ARPA) recovery dollars; the expiration of non-permanent federal grants; and decisions from the Trump administration to cancel, claw back, or drastically restructure federal funding.
Now, the fallout is showing up in programs meant to keep communities safe. Communities that leaned on the historic infusion of ARPA money are confronting the end of that funding, just as the federal government moves to eliminate or shrink critical programs. On the ground, that means scaled-back disease surveillance, hospitals less ready for disasters, reduced violence prevention, and disinvestment in the type of infrastructure that helps communities withstand climate-driven disruption.
Though municipalities have always been vulnerable to policy swings in Washington, the current budget woes also reveal a consistent structural gap where cities, instead of absorbing a program’s costs into their regular budgets, rely on federal money as the financial foundation rather than its scaffold.
Drawing on data from the Documenters Network across 23 communities, City Bureau examined how this perfect storm of budget cuts is unfolding around the country.
Understanding the ARPA cliff
At the heart of the expiring pool of federal money is the American Rescue Plan Act of 2021, which helped to prop up municipal budgets during the COVID-19 pandemic.
The law injected state and local governments with $350 billion in funding, with a little more than half going to state coffers, and the remaining $130 billion divided between cities and counties to cover expenses such as infrastructure investments, salaries for essential workers and other economic recovery. Once money was granted, municipalities had to allocate the funds by specific deadlines, or lose them entirely.
ARPA ends Dec. 31, the final deadline to spend allocated money before it is lost. There is no successor program in place.

But the looming ARPA sunset is not taking anyone by surprise, said Paula Worthington, an economist who focuses on municipal finance and serves as senior policy adviser at the Civic Federation, a Chicago-based economic research group.
“The funding streams for ARPA were well understood to be temporary — they had a beginning, middle and end,” Worthington said. Some municipalities winding down ARPA-funded programs were already experiencing financial pressure before the 2020 pandemic, Worthington added.
Despite ARPA’s planned end point, what makes it particularly difficult is what couldn’t be predicted back in 2021: the timeline overlapping the One Big Beautiful Bill Act, or H.R. 1, which took effect in July 2025 and marks one of the steepest reductions to the U.S. social safety net in decades, Worthington said.
When ARPA ends in December, major changes to Medicaid ordered by the Trump administration will take effect the next day. Changes including work requirements for able-bodied adults, and twice-annual eligibility renewal — along with at least $800 billion estimated federal spending cuts to Medicaid over the next decade — are expected to make the health insurance program harder and more expensive for state and local governments to administer, while dramatically reducing free or low-cost coverage for vulnerable people.
“H.R. 1 created significant disruptions to how federal support to states, counties and cities — and even school districts — is going to work,” Worthington said. “There have been a lot of efforts, in various ways, to claw back money that was already sort of agreed upon to go from the federal government to these sub-national governments and agencies — and the waters are choppy.”
Cancelled clinics, lost programs
The funding storm is falling especially hard on safety-net hospitals and public health departments — and with uneven outcomes.
In March 2025, the U.S. Department of Health and Human Services under Trump quickly cancelled nearly 700 Centers for Disease Control and Prevention grants nationwide. The move evaporated more than $11 billion for awardees including local public health departments to track disease, expand vaccinations and modernize disease detection systems.
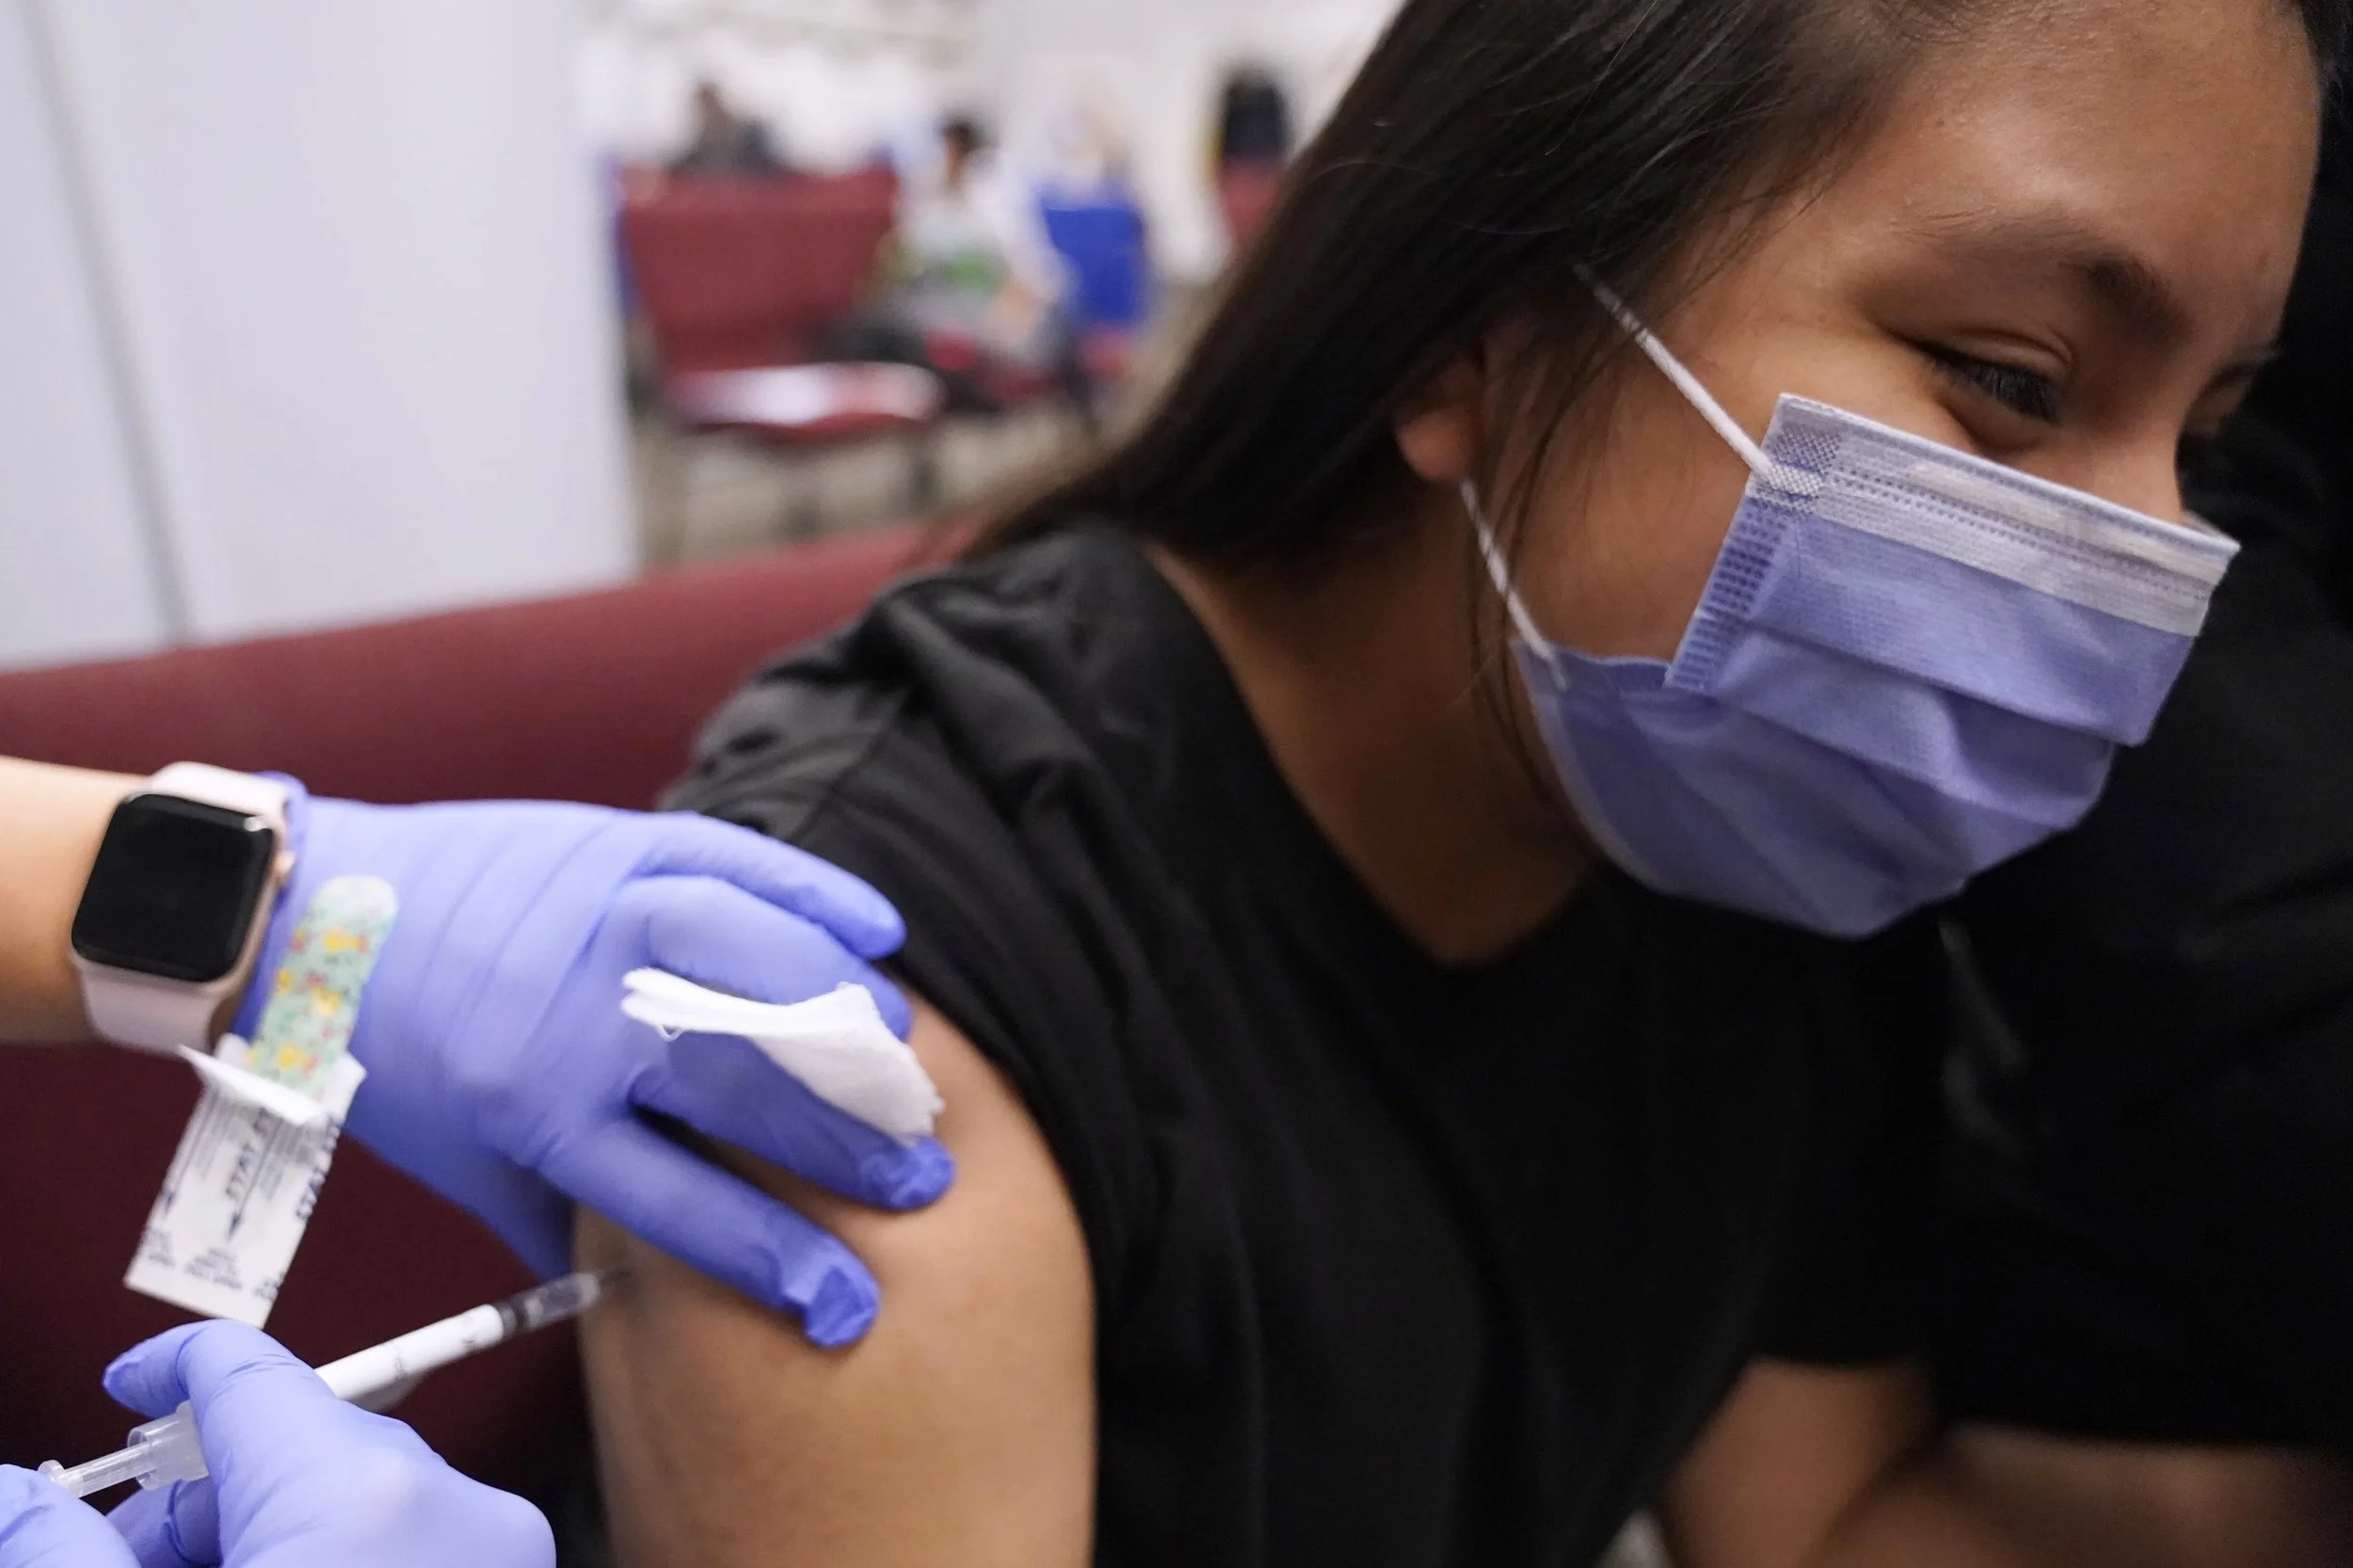
Krystal Salgado, 11, receives her second dose of the Pfizer COVID-19 vaccine from Lurie Children's hospital registered nurse Elvia Cervantes at Northwest Community Church in Chicago, Saturday, Dec. 11, 2021. (AP Photo/Nam Y. Huh)
In Chicago, which has one of the largest municipal public health departments in the country and one that primarily relies on federal funding, the abrupt grant cuts prompted warnings to residents from local health officials to brace for reductions: fewer immunization clinics, reduced infectious disease monitoring (HIV and COVID-19 among them), decreased lab capacity to test for emerging diseases, and less training to prevent disease spread in places like nursing homes, day cares and shelters.
In San Diego, further contributing to the instability, federal pullback of public health funding coincided with a loss of Ryan White HIV/AIDS Program money due to what county leaders described as a “fluke” in failing to spend use-it-or-lose-it funds. San Diego County consequently had to relinquish $1.6 million in federal money that helped low-income people living with HIV and AIDS receive temporary housing assistance and primary medical care, according to San Diego Documenters at inewsource.
The loss came as San Diego County was grappling with a $40 million pullback of CDC money for its new Public Health Lab meant to bolster the county’s response to transmissible disease, including HIV, according to Fox 5 San Diego.
But the multidimensional funding squeeze has been most severe in safety-net hospitals across the country.
With more healthcare programs losing money and healthcare costs for patients rising, the need for care is funneling into hospital systems like Hennepin County Medical Center in the Twin Cities and Eskenazi Health in Indianapolis. Both hospitals are among nearly 450 safety-net facilities facing heightened risk of closure due to changes to federal Medicaid spending that have reduced reimbursement for uninsured patient care, according to a 2026 analysis by the nonprofit accountability group Public Citizen.
Lisa Harris, CEO of Eskenazi Health, said in May that federal cuts and worsening disinvestment was making healthcare affordability so difficult that in a city where the median household income hovers just above $66,000, even households where income topped $90,000 were struggling to afford healthcare.
Some cuts have been successfully challenged in court or via lobbying; the Trump administration and House Republicans’ attempt to end federal funding of key components of the Ryan White HIV/AIDS Program was ultimately reversed by Congress — but the program now faces a year-to-year fight for renewal.
The impact of the fiscal storm has also been shaped by who has fought against it: an analysis by KFF Health News found that while Democrat- and Republican-led states faced equal funding disruption, nearly 80% of grant cuts were restored in blue states, more of which challenged the cuts in federal court.
Cuts squeeze violence prevention
When the U.S. Department of Justice’s Office of Justice Programs terminated public safety grants in two waves in spring 2025, community violence intervention programs were among the hardest hit.

Task force members and members of the public listen during the Gender Based Violence Task Force meeting on Wednesday, May 13, 2026, at City Hall in Chicago. (Photo: Anastasia Busby/City Bureau)
In Chicago, domestic violence services faced a 40% cut in the mayor’s proposed 2026 budget after ARPA funds ran out, Chicago Documenters reported. While alders pushed to restore the budget, it still lags behind demand for those services. Following national trends, homicides in cities like Chicago have dropped dramatically in recent years, but not all violence rates have followed that decrease: the proportion of domestic-related homicides rose 13% in 2025 compared to the year before, CBS News reported.
Perfect Storm: Funding cuts leave Chicago’s domestic violence survivors stranded
Minneapolis was hard hit by cuts to DHS violence prevention grants related to terrorism and mass shootings. According to Minneapolis Documenters at MinnPost, the area lost $2.7 million in DHS grants and $67,000 for a targeted violence and terrorism prevention program one month before the shooting at a Catholic school in Minneapolis last year — a move that spurred new criticism of how community safety was being negatively affected by federal disinvestment.
When funding cuts hit the Cuyahoga County Office of Violence Prevention in Cleveland, the burden was again shifted to local agencies. Cuyahoga County announced three $15,000 grants to local community groups.
The county Office of Violence Prevention did not respond to multiple requests for comment on how the federal cuts reshaped the program, but its administrator, Myesha Watkins, told Signal Cleveland in July that one-time $15,000 grants would not solve long-term funding needs for anti-violence groups. As an example, Watkins cited her former group, Cleveland Peacemakers, which spent $900,000 in 2024 on work such as mentorship programs, job training and street-level intervention.
Disaster preparedness wanes
For nearly 50 years, money for local disaster preparedness has typically flowed from the federal government to help municipalities train first responders for extreme weather or mass casualty events, build emergency operation centers, and shore up public infrastructure like warning systems, public transit and water treatment facilities.
But in the second Trump administration, the federal government has sharply reduced disaster preparedness and resilience funding as it moved to dramatically restructure the Federal Emergency Management Agency, shifting the responsibility to states.
The budget strain on a state has been exacerbated in places like Illinois when the federal government rejects requests for disaster relief funding. The federal government continues to reject state appeals on behalf of Chicago and Cook County for federal disaster relief following massive floods in 2025. In response, the Cook County Board absorbed a portion of the costs and approved a $15 million local relief program to help residents repair their homes.
The federal government has been repeatedly sued for withholding and clawing back more than $885 million in active funding for programs that include the Next Generation Warning System, which modernizes public emergency alerts; the Emergency Food and Shelter Program; and infrastructure resilience projects in both urban and rural communities.
But whether state and local governments stepped in with fractional funding to keep projects from collapsing or federal courts ordered the funding restored, the volatility creates ongoing challenges.
The Klickitat Valley Health hospital in rural Goldendale, Washington, experienced a funding roller coaster when FEMA canceled the Building Resilient Infrastructure and Communities Program (BRIC) in April 2025, jeopardizing the hospital’s $9.8 million plan to build battery storage for renewable energy. Though some states who sued the government saw grants reactivated, the delay made the project more expensive in the long run, said Jonathan Lewis, who directs support services for Klickitat Valley Health.
“Losing that momentum of being ready to roll and now just completely having to start from scratch because of those cost increases — we’re going to have to do a significant amount of redesign work,” Lewis said.
“We were all ready to get that project in place,” he added. “Now, the price of solar modules has gone up. There’s lots of upward or ‘bad’ pressure on solar that has impacted the project enormously, like the cost of labor going up considerably.”
The delays also cost Klickitat Valley Health an investment tax credit of 30% after it expired in 2025. The changes have eaten into the restored budget to the degree that leaders scaled back the project: Initially it was slated to produce about a megawatt of solar energy and two megawatts of battery power. Lewis anticipates the final project will generate about 70% of that.
The difference, Lewis said, was meaningful considering the project’s original goal was grid resiliency in the face of climate disasters like wildfires and intense winter storms.
In larger metros like Detroit, Documenters with Outlier Media noted that proposed cuts are affecting disaster preparedness of a different kind: how well hospitals in major population hubs who rely on federal funding can craft large-scale disaster response plans and test their ability to scale up capacity in an emergency.
Cuts to the Hospital Preparedness Program have funneled down to initiatives such as the Michigan Emergency Drug Delivery Resource Utilization Network (MEDDRUN), which maintains strategic stockpiles of antidotes to cyanide, nerve agents and organo-phosphates throughout Michigan in case of emergencies. Detroit Documenters told WDET last year the affected programs also fund efforts like burn surge planning in the event of a mass casualty or burn situation.
The fate of the funding remains uncertain more than a year after the cut was proposed, leaving communities unsure of how to craft future budgets.
Lewis, of Klickitat Valley Health in Oregon, said his organization plans to double down on grant-writing efforts given the uncertainty of federal funding.
“We saw the federal government as a trusted, reliable partner,” Lewis said. “And a lot of that trust has been broken.”
This article originally published with Next City.
Kim Bellware is a multimedia journalist who specializes in reporting that brings context, empathy and nuance to stories involving violence, trauma and conflict. She previously covered national breaking news for The Washington Post, mentored and led teams of Civic Reporting fellows at City Bureau, and has contributed as a freelance journalist to publications including The New York Times, The Atlantic, New York Magazine, and Rolling Stone.
Reporting for this article included the use of artificial intelligence to surface examples of funding cuts from City Bureau’s database of Documenters notes. All information included in this article was independently analyzed and verified by the reporter.
Support City Bureau’s work to reimagine local news by becoming a recurring donor today.